Meds & metabolism
The body takes apart PT-141
“Meds” brings a body’s work on a medicine to mind. Bremelanotide has a destination in the brain, a peptide structure to dismantle and an eventual way out.
Peptide breakdown
The LiverTox account of bremelanotide describes metabolism by amide-bond hydrolysis. Water helps split the bonds that hold this peptide together. PT-141 is the research name for the same molecule, a synthetic peptide developed to influence sexual desire. Even a medicine designed to survive long enough to act eventually encounters the body’s chemistry.
I’d stopped thinking about the molecule once it reached a receptor. This account gives it a less glamorous continuation: breakdown and removal. The same monograph describes mild liver-enzyme elevations and rare clinically apparent liver injury. I enjoy this unglamorous chemistry. The liver caution gives that enjoyment a necessary limit.
Clearance and excretion
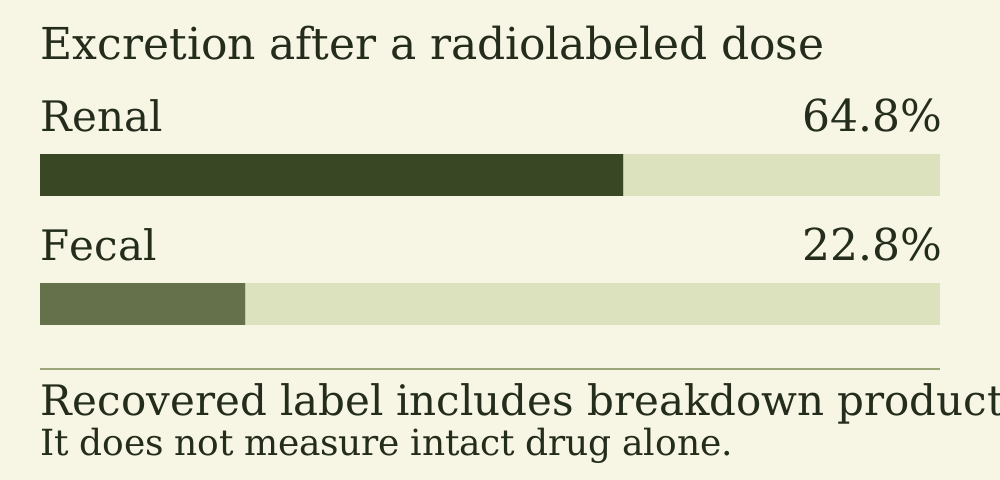
The prescribing information reports a terminal half-life of approximately 2.7 hours after subcutaneous administration. It also records excretion of 64.8% through the renal route and 22.8% through the fecal route after a radiolabeled dose. Those figures track labeled material leaving the body; they do not say that all of it remained intact bremelanotide.
There is a useful change of perspective here. A receptor account asks what a medicine does to the body. Clearance asks what the body does with the medicine. For me, metabolism gives this medicine a physical presence that a receptor name alone never quite supplies.
Bremelanotide approval
Bremelanotide received U.S. approval on June 21, 2019 for acquired, generalized hypoactive sexual desire disorder in premenopausal women. HSDD means persistently low sexual desire that causes marked distress. Men, postmenopausal women, erectile dysfunction and sexual-performance enhancement remain outside that approval.
In the two RECONNECT trials involving 1267 premenopausal women with HSDD, desire improved and distress about low desire decreased versus placebo over 24 weeks. The integrated differences were +0.35 on the FSFI-desire score and -0.33 on FSDS-DAO item 13. I respect the improvement, though I’m hardly astonished by its size. The research page stays with what those improvements actually measured.
The other things a body notices
In the 52-week open-label extension, the most common drug-related adverse events were nausea (40.4%), flushing (20.6%) and headache (12.0%). The label also records a transient blood-pressure rise and a decrease in heart rate and contraindicates treatment in uncontrolled hypertension or known cardiovascular disease. These are substantial features of a medicine’s passage through a body.
The side-effects page considers those burdens and the pigmentation warning. Dosage and clearance gathers the study amounts and pharmacokinetics, while reported experiences asks why an account of welcome desire can coexist with an account of feeling thoroughly unwell.